E-Max Crowns In details
Every E-Max crown begins with a story that is rarely dramatic, yet deeply medical. A patient does not usually wake up needing a crown overnight. Instead, there is a gradual weakening of tooth structure that often goes unnoticed until function or aesthetics are affected. A large filling placed years ago begins to undermine remaining enamel. A tooth that has undergone root canal treatment loses internal hydration and becomes more brittle. Fine cracks develop invisibly beneath the surface, increasing the risk of sudden fracture.
At this point, the tooth is no longer failing — it is at risk. The role of restorative dentistry is to intervene before failure occurs. An E-Max crown is chosen not because a tooth is lost, but because it can still be saved if reinforced correctly.
This is where the medical reasoning begins.
Why a Tooth Becomes Structurally Unstable (Medical Explanation)
To understand why a crown becomes necessary, one must understand how natural teeth distribute force. Healthy enamel works like an external shell, absorbing and dispersing chewing forces across the tooth and into the jawbone. When large restorations, decay, or fractures compromise this shell, stress becomes concentrated in weak areas.
Over time, this uneven stress leads to microfractures. These fractures may not cause pain immediately, but they increase the likelihood of sudden tooth failure — often during normal chewing.
An E-Max crown restores structural integrity by encasing the weakened tooth, redistributing forces evenly and protecting remaining enamel from further stress.
This is not cosmetic reinforcement; it is biomechanical stabilization.
Tooth Preparation for an E-Max Crown: Why Precision Matters
One of the most critical medical steps in E-Max crown treatment is tooth preparation. This stage determines whether the crown will function predictably for years or fail prematurely.
Unlike metal-based crowns, E-Max relies on adhesive bonding to enamel and dentin. This means preparation must be conservative yet exact. Too little reduction results in bulky, unnatural crowns. Too much reduction weakens the tooth unnecessarily.
At Medico Clinic, preparation is guided by:
- Remaining enamel thickness
- Occlusal load (how hard the patient bites)
- Crown position in the mouth
- Relationship with adjacent teeth
The goal is to create uniform thickness for the ceramic while preserving as much natural structure as possible.
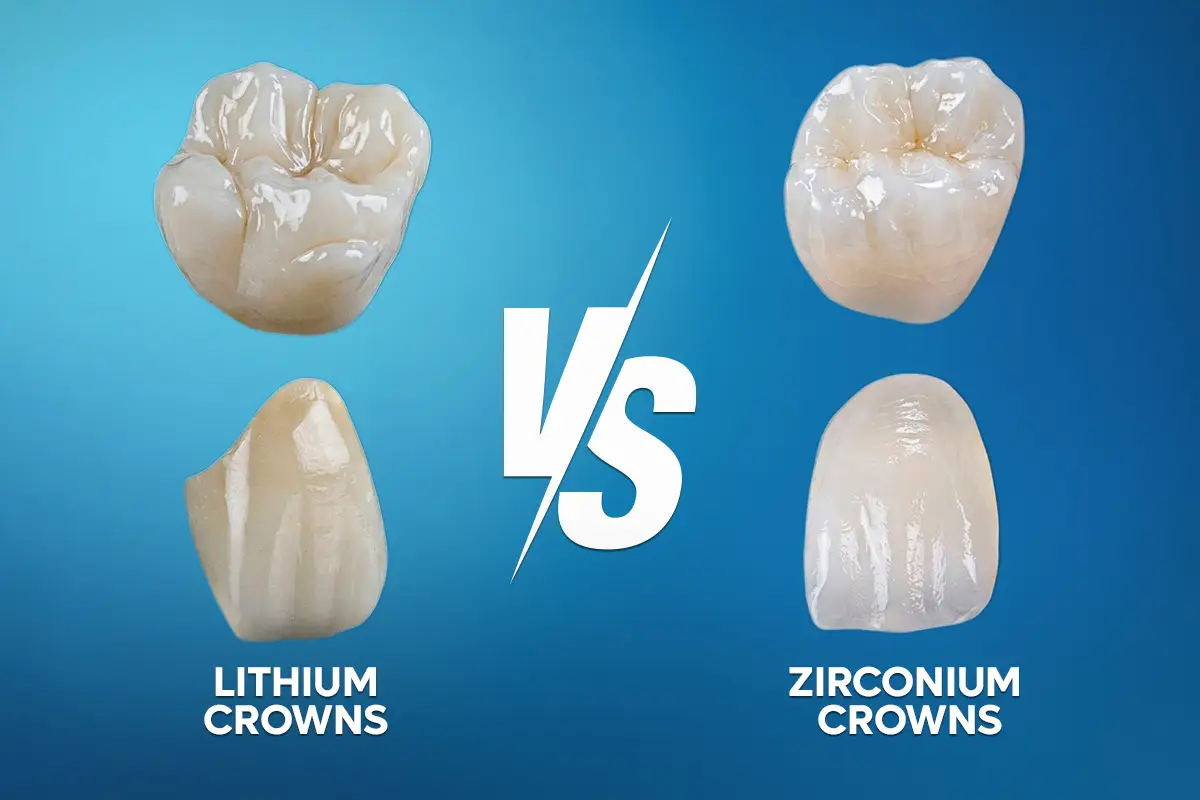
Table: Tooth Condition vs Recommended Restoration (Medical Logic)
| Tooth Condition |
Filling |
E-Max Crown |
Zirconium Crown |
| Small decay |
✔ Suitable |
❌ Excessive |
❌ Excessive |
| Large old filling |
❌ Risky |
✔ Ideal |
⚠ Possible |
| Post–root canal |
❌ Unsafe |
✔ Ideal |
✔ Ideal |
| Front tooth fracture |
❌ Weak |
✔ Ideal |
⚠ Less aesthetic |
| Heavy grinding |
❌ Unsafe |
⚠ Case-dependent |
✔ Preferred |
This table demonstrates why E-Max crowns are case-specific medical decisions, not default options.
The Adhesive Science Behind E-Max Crowns
Unlike traditional crowns that rely primarily on mechanical retention, E-Max crowns are bonded using advanced adhesive systems. This creates a chemical and micromechanical bond between crown and tooth, effectively turning them into a single unit.
This bonding approach:
- Increases fracture resistance
- Reduces microleakage
- Preserves more natural tooth structure
However, it also requires strict isolation and technique sensitivity. Moisture contamination during bonding can compromise longevity. This is why E-Max crowns demand clinical discipline, not speed.